Airborne Aerosols 201 Expert Forum
MaskTogetherAmerica warmly invites you to register for 4 Q&A sessions (Thu, Dec 3, 5-7PM ET) to discuss the latest in aerosol transmission and multi-layer prevention with 4 experts.
Schedule:
- 5:00 PM | How aerosol science can limit airborne disease transmission
Dr. Allen Haddrell, Research Fellow, University of Bristol - 5:33 PM | Recent advances in air quality interventions that would be of practical benefit to high-risk patients
Ms. Jill Heins-Nesvold, MS, MBA, National Director of Lung Health, American Lung Association - 6:05 PM | How data quality, consistency, frequency and reporting affect airborne transmission
Dr. Michael Hoerger, PhD, MSCR, MBA, MaskTogetherAmerica Advisor, Health Psychology and Population Sciences Expert, Professor, Tulane University - 6:40 PM | Mask Fit Testing & Selection (Especially for Children)
Mish, Mask Fit Testing Expert, MaskTogetherColorado (Presented by Professor Maria Gillespie)
The Urgency to Fight for Airborne Precautions
The hypothesis that a SARS-CoV-2 viral infection can damage lungs or initiate and accelerate serious chronic conditions—including lung cancer—is no longer just a collection of anecdotal case reports. Recent studies [1-16] have unveiled the primary pathways through which respiratory infections can lead to life-threatening damage across a human’s organ systems. The shared experiences of patients developing new chronic illnesses or receiving sudden cancer diagnoses post COVID infection are driving a massive paradigm shift. Pulmonology increasingly recognizes that acute viral insults can completely rewrite a patient’s long-term chronic disease trajectory.
To address the vacuum of awareness regarding airborne transmission (transmission via microscopic aerosols that float and linger in the air), we must expand the list of airborne-precaution-required pathogens beyond measles, herpes zoster (chickenpox), and Mycobacterium tuberculosis (TB). The debate about whether COVID is airborne must end. SARS-CoV-2 spreads through both airborne and droplet routes.
As the U.S. Environmental Protection Agency (EPA) explicitly states regarding the virus: “The particles can also linger in the air after a person has left the room – they can remain airborne for hours in some cases.”
The U.S. CDC officially recognized this mechanism in peer-reviewed data published in its own Emerging Infectious Diseases journal in 2022, which documented clear evidence of airborne aerosol transmission. However, its subsequent guidance published on June 13, 2024 focused heavily on droplets, ambiguously shying away from mentioning aerosol transmission and how long the virus remains contagious in the air.
Following years of pushback from aerosol scientists, the World Health Organization (WHO) formally overhauled its transmission definitions. In their Global Technical Consultation Report on Proposed Terminology for Pathogens That Transmit Through the Air, the agency discarded the old "droplet vs. airborne" dichotomy. The WHO's updated framework explicitly groups COVID-19, measles, influenza, and tuberculosis under the same fundamental category: pathogens whose main mode of transmission is "airborne transmission or inhalation" of Infectious Respiratory Particles (IRPs) that travel through or remain suspended in the air, regardless of distance or size. This is because “IRPs exist on a continuous spectrum of sizes, and no single cut-off point should be applied to distinguish smaller from larger particles.”
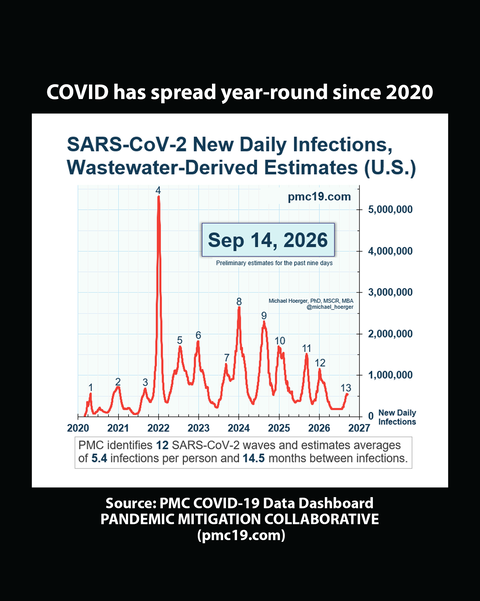
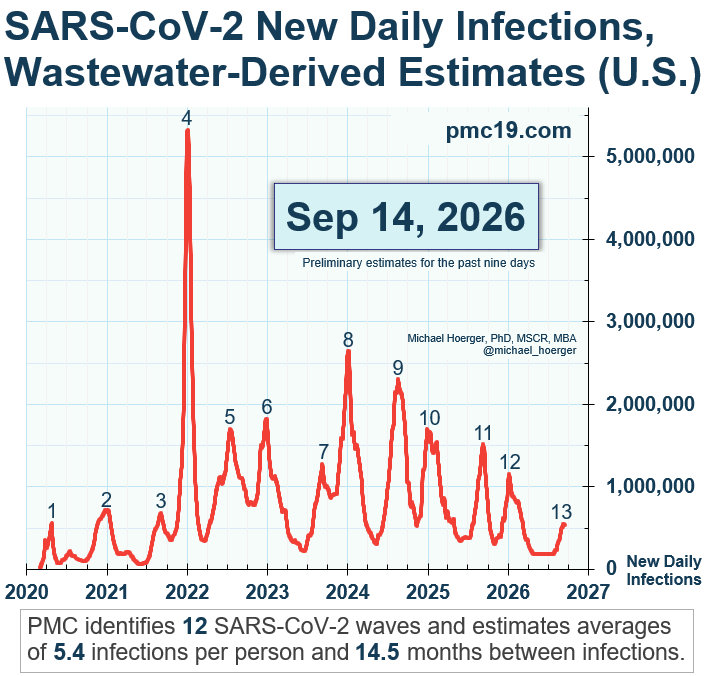
However, some experts criticized the WHO's new framework for COVID as complex, unrealistic, and ultimately confusing. Critics found that the terms weakened the direct link between the physical behavior of pathogens and essential control measures—especially when mitigating COVID requires robust ventilation, widespread use of N95 masks, and airborne isolation rooms (Global Biodefense). COVID has spread year-round since 2020, fueling an unprecedented rise in severe chronic illnesses globally. It is difficult to accept the WHO’s refusal to simply declare: COVID is airborne.
Aerosol Transmission Occurs at Short Distances
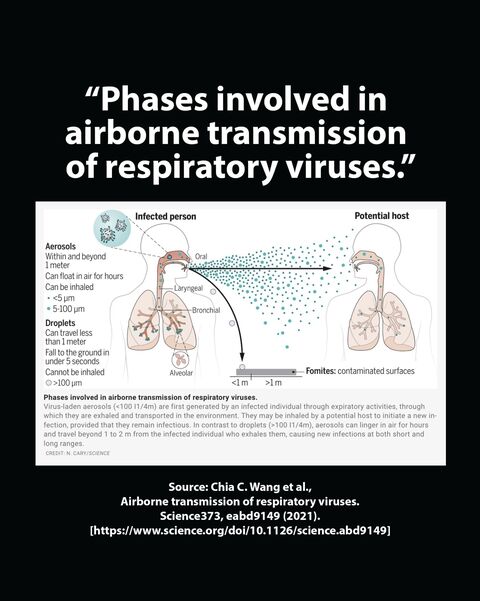
In a landmark article in Science, aerosol experts argued that "the historical definition of airborne transmission ignores the possibility that aerosols can also be inhaled at close range to an infected person, where exposure is more likely because exhaled aerosols are more concentrated closer to the person emitting them." They proposed changing the size guideline of an airborne particle from 5 μm to 100 μm, as 100 μm represents the largest particles that remain suspended in still air for more than 5 seconds (dropped from a height of 1.5 meters). A 100 μm particle can easily travel beyond 1 meter from an infectious individual to another person, causing infection through inhalation (Science, Wang et al., 2021, the 2nd image).
We must also account for airborne pathogens contracted from animals—such as H5N1 bird flu and hantavirus—as well as those from the environment, including infectious fungi like Aspergillus, Valley Fever, Histoplasmosis, and Blastomycosis. Fungal pathogens travel as dry, naturally microscopic spores. They are obligate airborne pathogens, inherently designed by nature to float on air currents for extended periods, making them textbook examples of airborne threats.
Practicing the Precautionary Principle
As detailed in NIH analyses, the precautionary principle applies directly to public health policy. In facing the emergence of new outbreaks, governments should assume that all respiratory pathogens are airborne until proven otherwise. A precautionary stance calls for immediate interventions like masking and ventilation rather than waiting for definitive transmission proof. A precautionary approach to deciding COVID’s route of exposure would have ensured that “the full range of relevant scientific disciplines was included in the deliberations—not only clinical specialties like infectious disease but also aerosol science, environmental epidemiology, and occupational hygiene” (Kriebel et al., 2025).
To educate the public about a layered approach to mitigation, we must start by acknowledging that common pathogens spread through aerosols. Airborne precautions apply to patients known or suspected to be infected with microorganisms transmitted by airborne droplet nuclei. Preventing airborne transmission requires well-fitting N95 respirators, specialized ventilation, and proper air handling.
Infectious diseases will continue to emerge as a part of nature, fueled by global warming. Learning from the catastrophic loss of human life in the ongoing SARS-CoV-2 pandemic, public health must adopt the precautionary principle. As Dr. David Keegan, a family doctor in Canada who spoke at our Long COVID Defense Series, notes: “When there’s an emerging fire, we should assume the worst until we know for sure that the fire is out or it’s a false alarm before telling everyone everything is okay.”
Dr. Keegan emphasizes that failing to manage COVID-19 as an airborne disease likely caused tens of millions of deaths and potentially left 1 billion people impacted by post-COVID conditions. "SARS-CoV-2 enters through the respiratory mucosa and induces vasculitis (inflammation of small blood vessels) across every organ. It’s not discriminatory. Every organ’s small blood vessels are at risk for severe inflammation and damage." [3, 4, 5, 12]. Preventing every single COVID infection matters.
While public health agencies frequently advise people to wash their hands and disinfect surfaces—which are good baseline hygiene practices—these measures alone will not prevent the spread of respiratory pathogens. Without educating the public on the fundamental reality of airborne transmission, people cannot understand why we must mitigate these threats or how to effectively choose and use the right tools. We need collective action to prevent outbreaks. This means cleaning indoor air with purifiers, ensuring that buildings, schools, healthcare facilities, and public transportation provide adequate ventilation, monitoring CO2 levels, normalizing mask-wearing, and actively encouraging prevention.
Furthermore, the intense stigma surrounding mask-wearing and vaccination is a direct threat to public health. It actively tears down the protections built over generations and destroys vital community trust. It is devastating to see vulnerable populations left behind—especially young children. A massive amount of misinformation suggests that children need to be exposed to viruses to build their immune systems. In reality, viruses are harmful; children need exposure to healthy microbes, not dangerous pathogens. [6, 7, 10, 12, 15, 16].
Measles-Induced Immune Disruption
A study that tracked 77 unvaccinated children before and after a natural measles infection provides hard clinical proof of biological harm [14]. By genetically sequencing the blood samples of these infected children, immunologists documented that the virus causes direct, lasting damage to the immune system. Utilizing a matching surrogate model, researchers demonstrated that this exposure drives a massive depletion of pre-existing immunity to the influenza virus, resulting in severe secondary flu infections. This clinical progression demonstrates that measles causes profound immune suppression, leaving individuals highly vulnerable to other opportunistic pathogens. These clinical findings mirror earlier population data, which showed secondary infections following a measles outbreak capable of disabling immune memory for two to three years, leading to a stark rise in childhood infectious disease mortality [15].
Pediatric Long COVID Actions Across All Organ Systems
Data published in Pediatria Polska (2026) reports that pediatric Long COVID is a complex, multi-systemic syndrome that causes widespread organ disruption. This includes severe nervous system impacts (cognitive dysfunction up to 81%, profound fatigue up to 87%, and sleep or mood disorders), respiratory distress (dyspnea up to 57%), and significant musculoskeletal weakness (myalgia up to 61%). The virus can also trigger cardiovascular variations, chest pain, and gastrointestinal injuries [6]. This diverse clinical presentation proves that a single acute viral insult can fundamentally destabilize a child's baseline systemic health.
[ See Table 1 (the 4th image). The most frequently reported long-COVID symptoms in children. Source: Long COVID-19 in children: a review of key information (Głowinkowska et al. 2026).]
In a Q&A published by the Johns Hopkins Bloomberg School of Public Health, Dr. Marsha Wills-Karp, Professor and Chair of Environmental Health and Engineering, debunked the misconception that viral exposure helps build the immune system: "Almost no virus is protective against allergic disease or other immune diseases. In fact, infections with viruses mostly either contribute to the development of those diseases or worsen them."
Conversely, Dr. Wills-Karp clarified that exposure to certain environmental bacteria can be beneficial. There are distinct routes to safely introduce these microbes [17-20] to strengthen rather than harm the microbiome—the delicate ecosystem where bacterial and human cells coexist. Therefore, while children should not be raised in a sterile environment, we must simultaneously improve indoor air quality to protect them from airborne viruses.
Public education is critical regarding the severe risks of repeat COVID-19 infections, particularly as pediatric Long COVID has become a top public health concern in the United States. To protect everyone in our community, especially those with compromised immune systems, we must take definitive action to establish standards for healthier, safer indoor environments—starting by cleaning the air we breathe.
About This Forum
This forum serves as a sequel to our past Airborne Aerosols 101 event and our two 2025 Clean Air Forums [21, 22, 23]. The community following our educational platform is largely composed of individuals with compromised immune systems, disabilities, and those living with Long COVID. In response to this growing crisis, we created a health defense guide a few years ago.
Unfortunately, the general population still faces limited access to public health data regarding the long-term harms of infection. We hope this forum—part of an educational campaign we launched in 2020—will continue to raise vital awareness about airborne disease prevention.
Register Now for Airborne Aerosols 201. Please email us with any questions.
Sources:
[8] Severe COVID-19, Flu Facilitate Lung Cancer Months or Years Later (UVA Health, 2026)
[9] Respiratory viral infections prime accelerated lung cancer growth (Cell, 2026).
Below are 13 sources on how to address the issue posed by the hygiene hypothesis: strengthening the immune system while avoiding exposure to pathogens. Some routes to address this are [17] probiotics and fermented foods, [18] vaccines, [19] bacterial lysates (often used in other countries, pieces of dead pathogenic bacteria to expose the immune system without infection risk), [20] exposure to healthy microbes in soil and in nature:
[17] Probiotics:
— Immune System Stimulation by Probiotic Microorganisms (Science and Nutrition, 2013).
[18] Vaccines:
– Pneumococcal bacteria (CDC, 2026)
[19] Lysates:
— Promising Immunomodulatory Effects of Bacterial Lysates in Allergic Diseases
(Frontiers in Immunology, 2022).
[20] Exposure to Microbes:
— Harnessing soil biodiversity to promote human health in cities (Npj Urban Sustainability, 2023).
MaskTogetherAmerica Clean Air Expert Forums: (21-23)
[21] Clean Air Emergency: Viral Surge + Wildfire Smoke Q&A Expert Forum
[22] Double Emergencies: Viral Surge + Wildfire Smoke Expert Forum
Access Info:
- Format: 4 Q&A sessions
- Presentations are spoken English
- Chat was open during the live virtual event
- Camera off for guests for security reasons
- Recording is edited and available on the website through Youtube and Facebook
Share this